Spravato vs TMS: Which Is Right for Treatment-Resistant Depression?

team • October 28, 2026

 Quick Answer: Spravato and TMS are both established, in-office treatments for depression that hasn't responded to antidepressants, and both are covered by most insurance plans with prior authorization. The core difference is simple: TMS is a drug-free magnetic stimulation treatment delivered in short daily sessions over about six weeks, while Spravato is an esketamine nasal spray taken alongside an oral antidepressant, with fewer visits but a two-hour monitoring period after each dose and no driving afterward. Neither is "better" across the board. The right choice depends on your history, your schedule, and clinical factors, and sometimes the answer is a combination. A clinician decides this with you.

If you've reached the point where standard antidepressants haven't worked, TMS and Spravato are probably the two names you keep running into. They're both serious options for treatment-resistant depression, and on the surface they can sound interchangeable. They aren't. They work in completely different ways, they ask different things of you week to week, and they suit different people. Here's an honest comparison to help you understand the trade-offs before you talk it through with a clinician.

What they have in common

Before the differences, it's worth being clear on where they overlap, because that overlap is real:

  • Both are used for treatment-resistant depression, meaning depression that hasn't improved enough after one or more antidepressants.
  • Both are delivered in-office rather than taken at home.
  • Both are covered by most major insurance plans when medical necessity criteria are met, which generally means a documented diagnosis, a history of failed antidepressant trials, and prior authorization.
  • Both have a track record and a defined protocol, rather than being experimental.

So this isn't a choice between a proven option and a gamble. It's a choice between two different proven approaches.

How they actually work

This is the fundamental split, and most of the other differences flow from it.

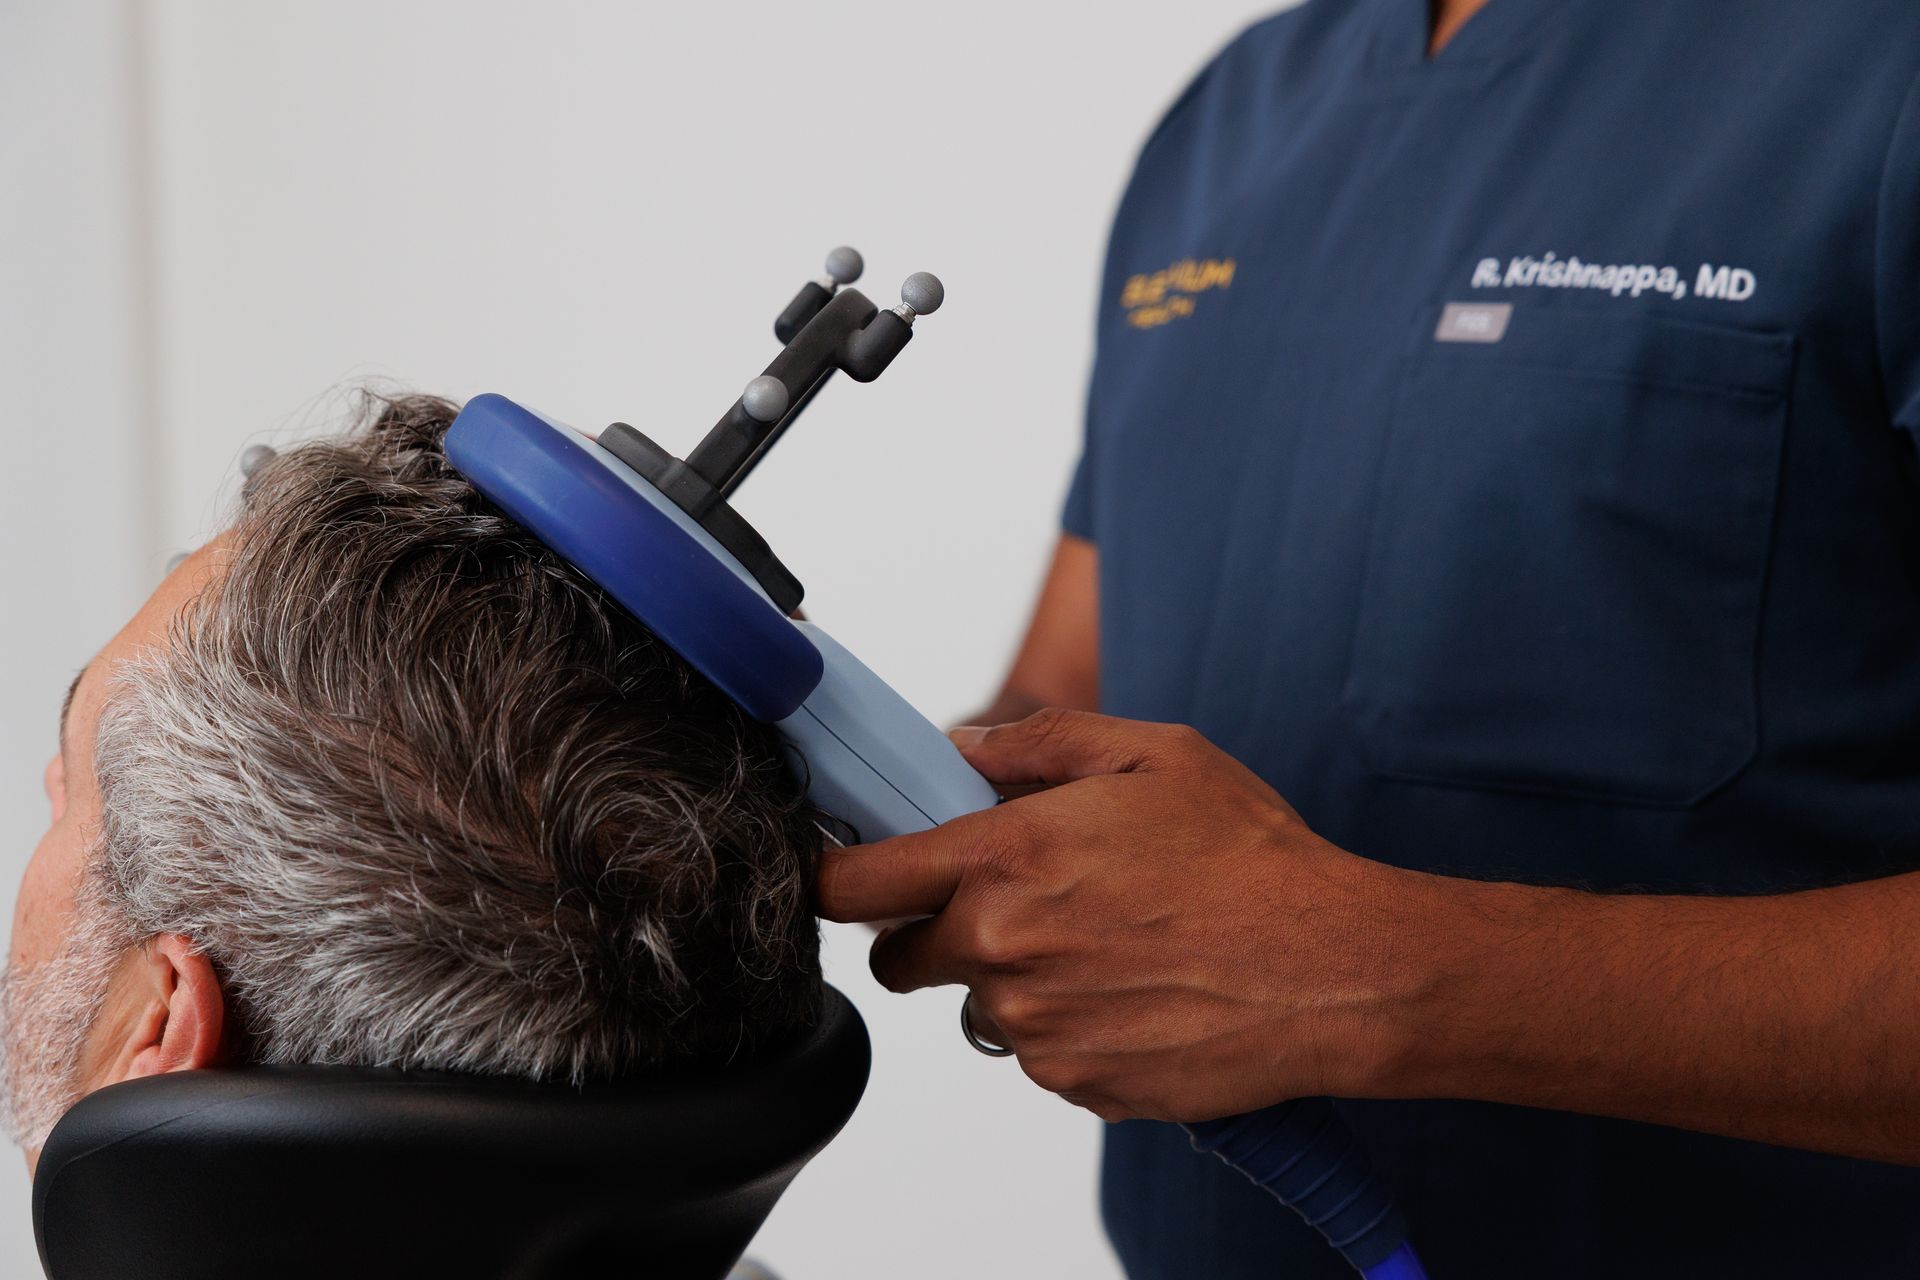
TMS (transcranial magnetic stimulation) is a drug-free, non-invasive treatment. A device delivers magnetic pulses to a targeted area of the brain involved in mood regulation. Nothing enters your system. It's FDA-cleared specifically for depression, and because the effect is targeted rather than systemic, it avoids the body-wide side effects associated with medication.

Spravato (esketamine) is a medication. It's an FDA-approved nasal spray, derived from ketamine, that acts on a different brain system than traditional antidepressants. It's taken alongside an oral antidepressant, not instead of one, and it's specifically approved both for treatment-resistant depression and for major depressive disorder with acute suicidal ideation.

That last point is a genuine differentiator. If acute suicidal thinking is part of the picture, Spravato carries an indication that TMS does not, and that can matter to the clinical decision.

What treatment looks like week to week

The day-to-day experience of each is quite different, and for many people this is the deciding factor.

With TMS, you come in five days a week for about six weeks, followed by a taper over roughly two more weeks. Each session is around 20 minutes of treatment, and you're usually in and out in about half an hour. There's no anesthesia and no recovery time, so you drive yourself home and carry on with your day. The commitment is the daily rhythm, not any single appointment.

With Spravato, you come in less often, but each visit takes longer. After your dose, there's a two-hour monitoring period where the team observes you before you leave, and you can't drive afterward, so you need someone to take you home. The visit schedule is more spread out than TMS, but each one takes up a chunk of the day and requires a ride.

So the honest framing is: TMS is frequent but quick and self-sufficient, while Spravato is less frequent but each session is longer and needs a driver.

Side effects compared

TMS side effects are usually limited to mild scalp discomfort or a light headache, mostly in the early sessions, and these tend to settle within the first week. Because nothing enters your system, there are no medication-type side effects.

Spravato side effects happen during and shortly after the session. The most common is a sense of dissociation (feeling somewhat detached from your body or surroundings), along with possible dizziness, nausea, sedation, or a temporary rise in blood pressure. This is exactly why the monitoring period exists. These effects are usually short-lived and fade the same day, but they make the treatment hours themselves more involved than a TMS session.

How fast each tends to work

People want to know which is faster, and the honest answer is that it varies by individual, but the general patterns differ.

TMS tends to work gradually. Most people don't notice much in the first week or two, and improvement, when it comes, usually builds across the course rather than arriving suddenly.

Spravato is often described as faster-acting, with some people noticing a shift within the early days of treatment. For someone who needs relief sooner rather than later, that pace can be a meaningful advantage.

Neither timeline is guaranteed, and neither treatment works for everyone. What matters is that your response is tracked over the course so you and your clinician can see whether it's helping rather than guessing.

Cost and coverage

Both treatments are covered by most major plans with prior authorization, though Spravato's authorization bar is generally a little higher. If insurance doesn't cover TMS, or you'd rather not go through authorization, TMS is also available as a self-pay option. Coverage specifics vary by plan and are confirmed at a benefits check before anything is scheduled, so cost shouldn't be a guessing game either way.

When one tends to make more sense

There's no formula here, and this is genuinely a clinical decision, but some factors tend to point one way or the other.

TMS often suits people who specifically want a drug-free option, who can commit to the daily schedule, and who would find the monitoring period and driving restriction of Spravato hard to arrange.

Spravato often suits people who want a potentially faster response, who can't manage daily visits but can arrange a ride for less frequent longer ones, and particularly where acute suicidal ideation is part of the clinical picture, given its specific indication there.

And it isn't always either/or. Depending on your situation, a clinician may suggest one first and the other later, or combine approaches. The goal is what works for you, not loyalty to a single method.

Frequently Asked Questions

Can I do both TMS and Spravato?

In some cases, yes. They work through different mechanisms, so a clinician may use them in sequence or together depending on your response and your situation. Whether that's appropriate is a clinical decision made on an individual basis.

Which one is more effective?

Both are established treatments for treatment-resistant depression, and effectiveness varies by individual rather than one being universally better. That's exactly why the choice is made with a clinician who can weigh your specific history, rather than from a general ranking.

Do I have to stop my antidepressant for either one?

Not necessarily. Spravato is specifically taken alongside an oral antidepressant. TMS doesn't require medication, but many people continue their existing treatment during it. Your clinician will advise based on your plan.

Which has fewer side effects?

They're different rather than simply more or less. TMS side effects are usually mild and limited to the treatment area, with nothing entering your system. Spravato's effects happen during the session and are the reason for the monitoring period, but they typically resolve the same day.

Share Article

Take the Doubt Out of TMS

Wondering if TMS is right for you? Take our quick quiz to get a personalized answer. No pressure, no commitment.

Take the Quiz →
A cell phone with a screen that says is tms right for me
Modern office with wooden desk, swivel chair, and orange lounge chair by large windows
By Ritesha Krishnappa • October 28, 2026
United Healthcare generally covers both TMS and Spravato for treatment-resistant depression when medical necessity criteria are met, though coverage details...
Eye exam in clinic with clinician using equipment while patient sits in chair and assistant observes nearby
By team • October 28, 2026
A standard course of TMS runs about six weeks of daily weekday sessions, followed by a taper over roughly two more weeks, for around 36 sessions in total. Ea...
Patient undergoing eye exam with clinician using equipment and another assistant beside a monitor
By Ritesha Krishnappa • September 8, 2026
Quick Answer: Treatment-resistant depression (TRD) is depression that hasn't improved after adequate trials of at least two antidepressants. It doesn't mean your depression is untreatable. It means the standard first steps haven't worked and it's time for a different kind of approach. In New Jersey, the on-label options include Spravato (FDA-approved specifically for TRD) and TMS (FDA-cleared for depression), alongside medication strategies and, off-label, ketamine. At Elevium Health in Florham Park, all of these are available. If antidepressants haven't worked for you, it's easy to conclude that nothing will. That conclusion is usually wrong. "Treatment-resistant" is a clinical category, not a verdict, and it points toward a specific set of next steps rather than a dead end. Here's what the term actually means, how to tell if it applies to you, and what the real options are in New Jersey. What treatment-resistant depression actually means The working definition is straightforward: depression that hasn't responded to at least two different antidepressants, each taken at an adequate dose for an adequate length of time. That last part matters more than people realize. An "adequate" trial generally means the right dose for a long enough stretch, usually several weeks, not a low dose stopped early. This distinction is important because a lot of depression labeled "resistant" was actually under-treated. If a medication was stopped after two weeks, taken at a starter dose that was never increased, or missed often enough that it never built up, it wasn't a fair test. Before treatment gets escalated, a good clinician checks whether the earlier attempts were genuinely adequate. Sometimes the answer changes the whole plan. Signs you might be dealing with TRD You might be looking at treatment-resistant depression if: You've tried two or more antidepressants and none brought meaningful relief. You get a partial response, some improvement, but never reach a point where you feel like yourself again. Symptoms return whenever a dose is changed or you switch between medications. Side effects forced you off medications before they had a real chance to work. Depression is still interfering with your work, sleep, or relationships despite ongoing treatment. None of these mean you're out of options. They mean the first-line approach, standard antidepressants, isn't the right tool on its own, and it's worth looking at treatments that work differently. The on-label options in New Jersey Two treatments are specifically indicated for this situation, which is what makes them the natural next step. Spravato (esketamine) . Spravato is FDA-approved specifically for treatment-resistant depression , which makes it one of the few treatments designed for exactly this problem. It's a nasal spray taken in-office alongside an oral antidepressant (the combination is part of the FDA labeling, not optional), and it acts on a different brain system than standard antidepressants. It's given at a REMS-certified center, which Elevium is, with a monitoring period after each dose. For many people with TRD, the appeal is speed, since it can work faster than a new oral antidepressant. You can read more on the Spravato page . TMS . Transcranial magnetic stimulation is FDA-cleared for depression and is a strong option when medications haven't worked, partly because it's drug-free and non-invasive. Rather than adding another medication to a system that hasn't responded to them, TMS uses magnetic pulses to stimulate a targeted brain region involved in mood. A standard course runs about six weeks, with no medication entering your system and no recovery time between sessions. More detail is on the TMS for depression page .
Two people in a lounge area talking on chairs, with a lamp and plant nearby.
By Ritesha Krishnappa • September 8, 2026
Quick Answer: If you want to treat depression without medication, the two established clinical options in New Jersey are TMS (an FDA-cleared, drug-free, non-invasive treatment) and psychotherapy. TMS is the most substantial non-medication option for depression that talk therapy alone hasn't resolved. At Elevium Health in Florham Park, both are available. One honest note up front: choosing a non-medication path doesn't have to mean ruling medication out forever, and for some people the best plan combines approaches. Plenty of people looking for depression treatment want to avoid medication, and for good reasons. Maybe antidepressants gave you side effects you couldn't live with. Maybe you tried several and none of them worked. Maybe you'd simply rather not take a daily pill if there's another route. Whatever brought you here, there are real, evidence-based options that don't involve medication. Here's what's actually available in New Jersey and how to think about the choice. Why people look for a non-medication option The reasons are usually practical, not ideological: Side effects. Weight changes, emotional blunting, sexual side effects, or fatigue make antidepressants a non-starter for some people. Medications didn't work. After one or more antidepressants that didn't help enough, a different kind of treatment makes more sense than another pill. Personal preference . Some people simply want to avoid daily medication, and that's a legitimate starting point for a conversation. None of these require justification. They're the everyday reasons people ask what else is out there. TMS: the leading non-medication treatment for depression Transcranial magnetic stimulation (TMS) is the most established drug-free treatment for depression, and it's FDA-cleared specifically for that use. It's non-invasive, meaning nothing is implanted, and no medication enters your system. Instead, a device delivers magnetic pulses to a targeted area of the brain (the dorsolateral prefrontal cortex, which is involved in mood regulation) to stimulate activity there. What it looks like in practice: you sit in a chair, awake, during each session. There's no anesthesia and no recovery time, and you can drive yourself home afterward. A standard course runs about six weeks of sessions, each around 20 minutes, followed by a short taper. Because the effect is targeted rather than systemic, TMS avoids the body-wide side effects that make antidepressants difficult for some people. The most common side effects are mild scalp discomfort or headache in the early sessions, which usually settle within the first week. For a lot of people avoiding medication, TMS is the treatment they didn't know existed. You can read more on the TMS for depression page .
Minimalist office desk with dual monitors, white chair, and framed abstract art on the wall.
By Ritesha Krishnappa • August 14, 2026
Quick Answer: Spravato experiences vary widely from person to person. Many people report relief faster than they got from traditional antidepressants, and reduced suicidal thoughts in particular. The trade-off is that each dose happens in-office with a two-hour monitoring period, and short-lived side effects like mild dissociation, dizziness, or a temporary rise in blood pressure are common during sessions. This post gives a balanced picture of both sides, so you know what to realistically expect. If you're searching for Spravato reviews, you're probably trying to answer the one question the marketing doesn't: what is this actually like? Online reviews skew toward extremes, the raves and the horror stories, with little in between. The honest version sits in the middle, and it depends a lot on who you are, what you've already been through, and what you expect going in. Here's a grounded look at what people tend to experience. Why Spravato reviews are so mixed Two things pull reviews to the extremes. First, the stakes are high. Spravato is generally used for treatment-resistant depression, meaning most people arrive after several antidepressants have already failed them. Expectations run high because the alternatives have run out. When it works, the relief can feel dramatic. When it doesn't, or when the side effects are rough, the disappointment lands harder than it would with a first-line treatment. Second, individual response varies. Some people notice a shift quickly, others feel little for weeks, and some don't respond at all. Two people can go through the same protocol and write opposite reviews, and both can be telling the truth about their own experience. What a Spravato session actually feels like This is the part reviews most often describe, and it surprises people who expect something like taking a pill at home. Spravato is a nasal spray taken in the office under supervision. After your dose, there's a two-hour monitoring period where the team checks on you before you leave. You can't drive afterward, so you'll need someone to take you home. During the session, it's common to feel "off" in ways that can be disorienting the first time: a sense of dissociation (feeling somewhat detached from your body or surroundings), dizziness, or drowsiness. For most people, these effects are short-lived and fade the same day. Knowing they're expected, and that you're being monitored the whole time, makes them far less alarming than they sound in a review written by someone who wasn't prepared for them. The positive experiences people report The most common theme in positive experiences is speed. Unlike traditional antidepressants that can take weeks to build up, some people report feeling a shift within hours or days of their early sessions. For someone who has spent years waiting on medications that never quite worked, that pace is the headline. The other recurring theme is reduced suicidal thinking. Spravato is specifically FDA-approved for major depressive disorder with acute suicidal ideation, and for some people the easing of those thoughts is the change that matters most, even before mood lifts more broadly. Responses are usually described as building over the first several weeks of treatment rather than arriving all at once.
Clinician fitting a blue head device onto a patient seated in a black chair
By Ritesha Krishnappa • August 14, 2026
Quick Answer: With insurance, TMS is covered by most plans when medical necessity criteria are met , and your out-of-pocket cost depends on your plan's copay, coinsurance, and deductible. Without insurance, a standard course of TMS at Elevium Health in New Jersey is priced at $9,600 for 36 sessions. Elevium is in-network with UnitedHealthcare/Optum and Horizon BCBS of New Jersey, and verifies your exact out-of-pocket cost in writing before treatment begins. Cost is usually the question that decides whether someone actually starts TMS, and it's also the hardest to get a straight answer on. This post lays out what TMS costs in New Jersey both ways (through insurance and self-pay), what changes the number, and how Elevium confirms your cost before you commit to anything. TMS cost with insurance Most major insurers cover TMS for treatment-resistant depression, so for many people the real question isn't "is it covered" but "what will I pay?" Your out-of-pocket cost comes down to your plan's structure: your deductible (how much you pay before coverage begins), your copay or coinsurance per session, and whether you've already met your deductible for the year. Learn More: Insurance Coverage  Two things determine whether coverage applies at all: Medical necessity. Carriers generally require a documented major depressive disorder diagnosis, a history of antidepressant trials that didn't work well enough, and prior authorization before treatment starts. In-network status. Elevium is in-network with UnitedHealthcare/Optum and Horizon BCBS of New Jersey, and is verifying additional carriers. If you have a different plan, ask, and the billing team will check it. The billing team runs the benefits check and handles prior authorization for you, then confirms your out-of-pocket cost in writing before anything is scheduled. You shouldn't have to guess at the number or discover it after the fact.
By Ritesha Krishnappa • July 3, 2026
Quick Answer: A TMS evaluation is the consultation that determines whether TMS is right for you before any treatment begins. At Elevium Health in Florham Park, New Jersey, it covers three things: a clinical assessment of your depression and treatment history, a medical safety screening for contraindications, and an insurance benefits check. It's not the treatment itself — it's the step that confirms you're a candidate, rules out safety risks, and sorts out coverage, so you can make the decision with the full picture in front of you. If you've been researching TMS, you've probably read plenty about what the sessions are like. The part that gets less attention is the evaluation - the step that actually decides whether you start. It matters more than people expect, because a thorough evaluation is what makes the rest of the process safe, personalized, and far less uncertain. Here's what a comprehensive TMS evaluation involves and why each part is there. Why the evaluation exists TMS isn't a first-line treatment , and it isn't right for everyone. The evaluation is how a clinician confirms three things before you commit time, money, or hope to a six-week course: Are you a candidate? TMS is used for treatment-resistant depression — typically when antidepressants haven't worked well enough or weren't tolerated. The evaluation confirms the diagnosis and treatment history that make TMS appropriate. Is it safe for you? A small number of conditions and implants make TMS unsafe. Screening for them protects you. What will it cost? Insurance coverage for TMS depends on meeting specific criteria. The evaluation is where that gets checked, before anything is scheduled. Skip any of these, and you risk starting a treatment you're not a fit for, weren't safe for, or didn't realize wouldn't be covered. That's why the evaluation is the step that turns a question into a confident decision. The clinical assessment This is the core of the visit. One of our psychiatrists builds a complete picture of your mental health and what's brought you here. Expect a real conversation rather than a checklist, covering: Your diagnosis and symptoms. When did things start, what does a difficult day look like, and how is depression affecting your daily life. Standardized depression rating scales are often used so progress can be measured objectively later. Your treatment history. Which antidepressants have you tried, at what doses, for how long, and why you stopped each? This matters clinically, and it matters for insurance - most carriers want documented evidence that medications were tried before they'll authorize TMS. Your goals. What "better" actually looks like for you. This shapes how treatment is planned and how progress is judged. The honesty of this conversation directly affects the quality of your plan, so it's worth coming prepared (more on that below).
By Ritesha Krishnappa • July 3, 2026
Quick Answer: Horizon Blue Cross Blue Shield of New Jersey generally covers TMS and Spravato for treatment-resistant depression when medical necessity criteria are met, but does not cover ketamine infusions, which are considered off-label. Elevium Health is in-network with Horizon BCBS of New Jersey, and the billing team runs your benefits check and handles prior authorization before treatment is scheduled — so you'll know what's covered before you commit to anything. If you've reached out about TMS, Spravato, or ketamine and you're covered by Horizon, the next question is almost always the same: what will my plan actually pay for? This post covers where Horizon BCBS of New Jersey typically lands on each treatment, what prior authorization involves, and how Elevium handles the paperwork so you're not the one chasing approvals. First, two things that trip people up "In-network" and "covered" are not the same thing. Elevium being in-network with Horizon means the practice has a contracted relationship with the carrier. Whether a specific treatment is paid for is a separate question that depends on your individual plan and on meeting medical necessity criteria. A treatment can be a covered benefit and still require prior authorization before it starts. Plan details vary, even within Horizon. Horizon administers many plan types — commercial, employer-sponsored, and others — and the specifics (which treatments need authorization, how many medication trials count, what documentation is required) differ between them. Anything below is directional. We confirm the exact terms of your plan at the benefits check. Learn More: Insurance Coverage Does Horizon BCBS of New Jersey cover TMS? For TMS, Horizon generally follows a treatment-resistant depression framework. That typically means a documented diagnosis of major depressive disorder (MDD), a history of antidepressant trials that didn't work well enough or weren't tolerated, and prior authorization before treatment begins. Horizon, like most carriers, also has specific criteria for what counts as an adequate medication trial — duration, dose, and adherence all factor in. TMS for depression is the most commonly covered use. Coverage for TMS for OCD is more variable and tends to require stronger documentation of symptom severity and prior treatment history. If OCD is the reason you're considering TMS, it's worth flagging specifically so we can check that part of your benefits carefully. Does Horizon BCBS of New Jersey cover Spravato? Spravato (esketamine) is FDA-approved for treatment-resistant depression and for major depressive disorder with acute suicidal ideation. Horizon generally covers it, but the prior authorization bar is usually higher than for TMS . Common requirements across plans include a documented MDD diagnosis, a history of failed antidepressant trials, and a concurrent oral antidepressant taken alongside Spravato - that last one is an FDA requirement, not just an insurance rule. Spravato also has to be delivered at a REMS-certified facility, which Elevium is, with a monitoring period after each dose. Where plans differ is in how many prior medication trials they require and how they handle continuation of treatment after the initial phase. Does Horizon BCBS of New Jersey cover ketamine? Generally, no. Ketamine infusion therapy is distinct from Spravato. While Spravato is an FDA-approved esketamine product, IV ketamine for depression is considered off-label, and Horizon — like most carriers — does not cover it. Ketamine at Elevium is a self-pay treatment. If insurance coverage is the deciding factor for you, Spravato is usually the better-covered esketamine option, and it's worth discussing which fits your situation before ruling anything out. You can also review treatment costs to understand the self-pay picture.
Counselor and client in a therapy office, seated across from each other during a conversation.
By Ritesha Krishnappa • May 29, 2026
Quick Answer: TMS is an FDA-cleared, non-invasive depression treatment for adolescents aged 15 and older when antidepressants haven't worked well enough . For parents, the decision usually comes down to four things: whether your teen meets clinical criteria, how it fits with their current therapist or psychiatrist, what insurance will cover, and what a course actually looks like day-to-day. This guide walks through each. If you've tried the conventional route — therapy, medication, or both — and your teen still isn't where you'd hoped, TMS is one of the newer options available in New Jersey. At Elevium Health in Florham Park, this guide is for the homework stage, before any decisions get made. When TMS Becomes a Reasonable Option TMS isn't usually the first treatment a teen tries. It enters the conversation when standard approaches haven't been enough - typically after at least one antidepressant trial that didn't work well enough or caused side effects your teen couldn't tolerate. Common situations where families start looking at TMS: A teen has been on SSRIs for several months with limited improvement Side effects (weight changes, sexual side effects, emotional blunting) are making medication a non-starter Your teen is engaged in therapy, but depression is still interfering with school, sleep, or relationships You and their psychiatrist want a non-medication option to add to the plan For adolescents, FDA guidance is that TMS is used alongside antidepressant medication, not as a replacement. Who Qualifies The FDA cleared TMS for adolescent depression for ages 15 and older . Practically, eligibility at Elevium depends on: Age: 15 or older Diagnosis: Major depressive disorder, confirmed by a treating clinician Treatment history: Usually a documented trial of at least one antidepressant Continuity of care: An existing child and adolescent psychiatrist or therapist who stays involved Concurrent medication: Your teen on (or starting) antidepressant medication during the course Safety screening: No metal implants in the head or neck, no recent adverse TMS events; history of seizures is a relative contraindication We don't currently offer psychotherapy or medication management to adolescents at Elevium, so your teen will need an outside therapist or psychiatrist willing to coordinate with our clinical team. Worth confirming that with their current providers before booking.
Five staff members stand behind a white reception desk in a modern clinic lobby.
By Ritesha Krishnappa • May 29, 2026
Quick Answer: Your first medication management appointment at Elevium Health runs about 60 minutes. The psychiatrist takes a full history, reviews any medications you've tried, and discusses your symptoms and goals. Sometimes you'll leave with a prescription that day; sometimes the right move is to gather more information first. Either way, you'll know what's happening next before you walk out. If you've filled out the contact form for medication management, you're probably weighing whether to book the appointment. This post walks through exactly what happens at that first visit — what you'll be asked, what gets decided, and what to bring — so you can show up without the unknowns getting in the way. Before the Appointment A few things to sort out in the days before: Confirm insurance and paperwork. You'll get intake forms in advance. Filling them out properly saves time at the appointment — incomplete forms mean the psychiatrist spends the first part of the session asking questions you already had answers to. Pull together your medication history. This is the single most useful thing you can bring. A simple list of: Any psychiatric medications you've tried (even years ago) Doses, if you remember them How long you took each one Why you stopped (didn't work, side effects, ran out, switched doctors) If you're not sure, pharmacy records or your previous prescriber's notes are gold. Don't worry if it's incomplete — the psychiatrist will fill in the gaps in conversation. But the more you can bring, the faster you get to a treatment plan that fits. Note any current medications. Including over-the-counter medications, supplements, and anything from another prescriber. Drug interactions matter, and the psychiatrist needs the full picture. What Happens During the Appointment The first appointment is longer than follow-ups — usually around 60 minutes - because the psychiatrist is building a complete picture of your mental health, your medical history, and what you're hoping to get out of treatment. The conversation tends to cover: Your symptoms and what brought you in. When did things start? What does a bad day look like? What makes it better or worse? This isn't a checklist — it's a real conversation, and you don't need to have it perfectly articulated. Most people don't. Your psychiatric and medical history. Previous diagnoses, hospitalizations, therapy history, family history of mental health conditions, and any physical health conditions that could affect medication choice (thyroid issues, cardiac history, kidney or liver function, pregnancy plans). What you've tried. Medications, therapy, lifestyle changes, alternative approaches. The psychiatrist isn't judging — they're learning what's worked, what hasn't, and where to start. Your goals. What does "better" look like for you? Sometimes that's "I want to stop crying every morning." Sometimes it's "I want to be present with my kids again." There's no wrong answer; this shapes the treatment plan. Risk and safety. Standard questions about any thoughts of self-harm or suicide. These are routine — every psychiatrist asks them — and honest answers help the psychiatrist make safer choices. What Gets Decided That Day Three things usually happen by the end of the appointment: A working diagnosis or impression. This may match what you've been told before, or it may be different. The psychiatrist will explain what they're seeing and why. A starting plan. Often this is a prescription — either a new medication or an adjustment to what you're already on. Sometimes the plan is to gather more information first (lab work, records from a previous provider) before prescribing. Either approach is normal. A follow-up schedule. Most people are seen again within two to four weeks of starting or adjusting medication. This is a closer follow-up than you might be used to, and it's intentional - the early weeks are when adjustments matter most.
A cell phone with a screen that says find your treatment fit

Take the Guesswork Out of Treatment

Answer a few quick questions to discover which treatment best fits your needs.

Take the Quiz →